Why Dentists Should Be Focusing on Myofunctional Therapy
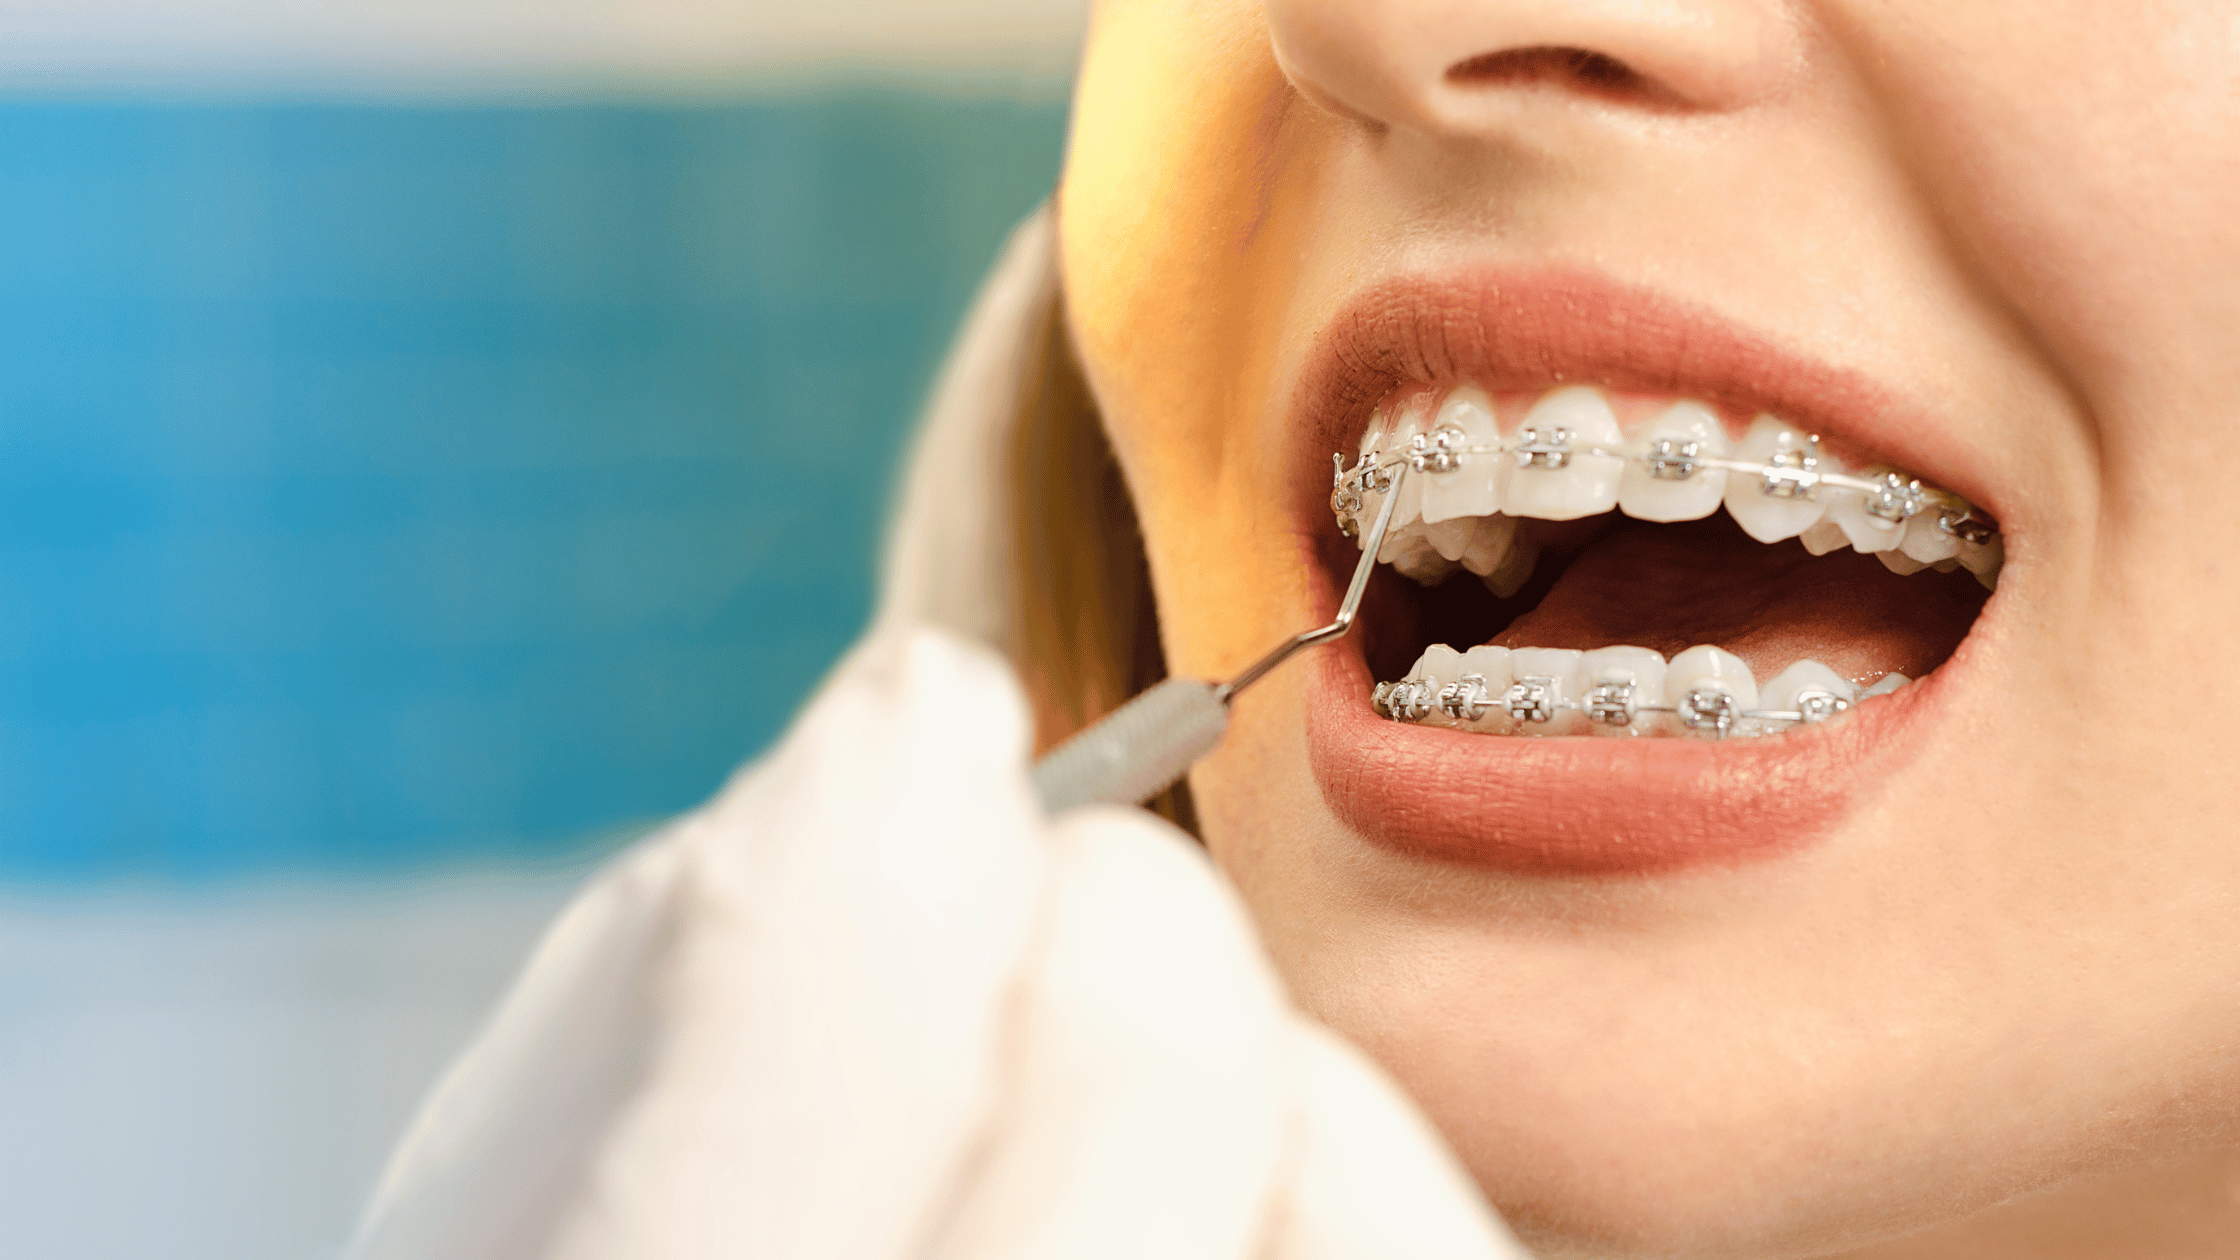
The brackets come off. The bite looks great. The retainer fits. BUT...six months later, the open bite is creeping back.
If you've seen this happen where are teeth relapsing, mouth breathing continuing, a patient who still can't rest with their lips togethe, the problem usually isn't the orthodontics. It's what's happening around the teeth, all day, every day, long after treatment ends.
The tongue, lips, cheeks, jaw, and breathing pattern don't stop working once a case is finished. They're active during swallowing, chewing, speaking, and rest and when their patterns don't match the new bite, the bite is the thing that gives.
That's the gap myofunctional therapy is built to close.
Orofacial myofunctional therapy (OMT) targets tongue resting posture, swallowing, lip function, chewing, and other orofacial behaviors. It doesn't replace dentistry or orthodontics. It addresses the functional patterns that structural treatment alone often can't reach. For dentists and orthodontists building an airway-focused dentistry approach, that distinction is the whole point: teeth are only one part of a system that includes muscle function and breathing.
What Is Myofunctional Therapy?
Myofunctional therapy is behavioral, neuromuscular therapy for the muscles of the face, mouth, and jaw. Depending on the patient, it may address:
Tongue resting posture
Lip closure and lip strength
Swallowing patterns
Chewing
Nasal breathing habits
Open-mouth posture
Tongue thrust
Oral habits
Orofacial coordination
Speech-related oral motor patterns
Jaw and facial muscle function
A myofunctional therapist looks at how these structures function together, rather than evaluating teeth in isolation which matters because the same patterns present before orthodontic treatment often persist afterward.
A patient can finish treatment with an improved bite and still:
Rest with the tongue low in the mouth
Push the tongue forward during swallowing
Breathe primarily through the mouth
Keep the lips apart at rest
Maintain an open-mouth posture
Have a persistent oral habit
Struggle to hold an appropriate tongue-to-palate resting position
None of these guarantee relapse on their own relapse is multifactorial, involving growth, periodontal and tissue factors, the original malocclusion, retention, and oral habits. But identifying functional patterns gives the dental team a fuller picture of why a case might not hold.
The Muscle Factor Behind the Bite
Teeth don't exist independently from the muscles around them. The tongue, lips, and cheeks interact with the teeth constantly, especially during the repetitive movement pattern of swallowing.
The clinically useful question isn't just:
"Where are the teeth?"
It's also:
"What is the mouth doing all day when the patient isn't thinking about it?" sitting quietly, sleeping, swallowing, eating, speaking, breathing, concentrating, exercising.
This matters most when a patient's functional pattern doesn't match the structural correction achieved. Picture a patient treated for anterior open bite: the bite improves, the brackets come off, the retainer goes in but the tongue still moves forward during swallowing and still sits low or forward at rest. That doesn't prove relapse is coming. It's a functional factor worth evaluating, especially with a history of open bite, tongue thrust, oral habits, or other myofunctional concerns.
Research has linked orofacial behaviors ,tongue thrusting, mouth breathing, prolonged sucking habits , with certain malocclusions, though the relationship is complex and not universal. That's exactly why a functional assessment adds value.
Tongue Posture and Open Bite: What Dentists Should Know
Tongue posture and open bite is one of the most frequently discussed reasons for collaboration between orthodontists and myofunctional therapists. Anterior open bite rarely has one cause contributing factors can include:
Skeletal growth patterns
Dental eruption patterns
Prolonged non-nutritive sucking habits
Tongue posture or tongue thrusting
Mouth breathing
Lip incompetence
Other orofacial functional patterns
A combination of genetic and environmental factors
Because of that, every open bite patient deserves individual evaluation. The goal isn't to reflexively blame the tongue . It's to determine whether oral function is contributing to the clinical picture. Myofunctional therapy isn't a universal answer for every open bite; it's one piece of a broader interdisciplinary evaluation when history and findings point that way.
What About Orthodontic Relapse?
Relapse is one of the biggest concerns for clinicians and patients alike, and it's rarely caused by a single factor. Long-term stability after open bite correction can be genuinely difficult to maintain, and the right approach depends on the underlying cause and patient characteristics which is one of the more consistent orthodontic relapse causes in the literature.
It helps to separate structural stability from functional stability. Orthodontics repositions teeth and surrounding structures. Myofunctional therapy addresses how the muscles and oral structures are actually being used. Both are pieces of the same system.
If a patient finishes treatment but still shows a significant functional pattern that predates it, previous open bite, persistent tongue thrust, low tongue resting posture, mouth breathing, open-mouth posture, poor lip closure, a history of prolonged thumb or pacifier use, that's worth a conversation about a myofunctional evaluation, not just closer monitoring.
Myofunctional Therapy Is Not a Replacement for Orthodontics
This is worth stating plainly: myofunctional therapy doesn't move teeth. It doesn't replace orthodontic diagnosis, retainers, or dental treatment, and it shouldn't be sold as a guarantee against relapse.
Think of it as another layer of care. The dentist or orthodontist manages structure. The myofunctional therapist addresses relevant function. Other specialists may join as needed, an ENT for chronic nasal obstruction, a sleep physician for significant sleep-disordered breathing, a speech-language pathologist for feeding or speech concerns. The patient doesn't have to choose between providers; care can be collaborative.
Why the Dental-Myofunctional Partnership Matters
Interdisciplinary care works best when each provider stays in their lane while communicating about the whole patient.
A dentist might flag: "This patient's bite is improving, but I'm concerned about tongue posture and persistent open-mouth posture."
A myofunctional therapist might add: "The patient is having difficulty maintaining a functional tongue resting position and shows a forward swallowing pattern."
That exchange shapes real decisions: whether therapy is appropriate, when it should start, what functional goals to target, whether additional medical evaluation is needed, how to monitor progress, and how to time therapy against orthodontic treatment. That's a different relationship than a one-way referral with no follow-up — the strongest partnerships have an actual referral pathway and ongoing communication.
When Should a Dentist Consider a Myofunctional Referral?
There's no single checklist, but certain findings make a referral worth considering.
1. Persistent open-mouth posture. Can the patient comfortably close their lips? How do they breathe? Where does the tongue rest? Is there nasal congestion, a history of enlarged tonsils or adenoids, snoring, or other airway concerns? Mouth breathing has multiple possible causes, so rule out the need for medical evaluation before assuming therapy alone is the answer.
2. Low or forward tongue resting posture. Where the tongue sits at rest — outside of eating or speaking — can be clinically informative, particularly alongside certain malocclusions. A myofunctional evaluation looks more closely at posture, mobility, strength, and coordination.
3. Tongue thrust or atypical swallowing pattern. When the tongue consistently moves forward during swallowing, especially with an open bite present, a functional evaluation helps identify why — mobility, awareness, strength, and coordination all factor in, not just the habit itself.
4. Difficulty maintaining lip closure. Some patients can close their lips on request but drift back to an open-mouth posture at rest. That gap is clinically useful information and may point to an underlying functional or airway issue.
5. Orthodontic relapse. When dental changes recur, review the whole picture: retainer use, oral habits, tongue posture, swallowing, breathing, lip posture, growth, previous treatment, and any changes in health or airway status.
6. Persistent oral habits. Thumb sucking, finger sucking, prolonged pacifier use, and similar habits can affect developing oral structures. When a habit persists alongside dental changes, myofunctional collaboration may be worth considering.
What Does a Myofunctional Evaluation Actually Look At?
For dentists who haven't worked closely with a myofunctional therapist, a comprehensive evaluation typically observes:
Resting posture — lip position, tongue position, tooth contact, nasal vs. mouth breathing
Swallowing — forward tongue movement, excessive lip or facial muscle activity, compensations
Tongue function — elevation, positioning, symmetry, coordination
Lip function — ability to maintain closure, overwork during swallowing
Breathing pattern — nasal comfort, persistent mouth breathing, signs warranting further airway evaluation
Chewing — efficiency and coordination
Speech — oral motor patterns that may relate to function
This evaluation complements what you're already seeing clinically — it doesn't replace it.
What Does the Research Say?
The evidence is encouraging in places, but incomplete, and it's worth being honest about that. A 2025 scoping review of OMT in orthodontic and orthognathic contexts — covering malocclusion, anterior open bite, and residual myofunctional disorders — found positive results in many individual studies, alongside real limitations in study design, follow-up length, and evidence quality. A separate scoping review of 58 studies found only 11 randomized controlled trials, concluding that high-level evidence is still insufficient to fully confirm OMT's effectiveness across the conditions studied. Earlier systematic reviews reached similar conclusions: potential benefit in select cases, but a limited evidence base with meaningful risk of bias.
That's why the accurate conversation isn't:
"Myofunctional therapy prevents orthodontic relapse."
It's:
"Certain orofacial functional patterns may be relevant to a patient's orthodontic presentation and stability. When those patterns are present, interdisciplinary evaluation and treatment may be appropriate."
That's a more clinically responsible way to frame collaboration — and a more credible one to bring up with patients.
Myofunctional Therapy Before, During, or After Orthodontics?
Timing is patient-specific. Some patients benefit from evaluation before treatment starts, to catch functional factors early. Others benefit from therapy running alongside orthodontic treatment. For others, the focus is establishing new functional patterns after treatment ends.
There's no universal timeline — but there is a universal requirement: communication. When the dentist and myofunctional therapist are working toward different goals without talking, the patient ends up confused. When everyone's aligned, the patient gets a coordinated experience instead of two disconnected treatment plans.
What Dentists Can Start Looking For Tomorrow
You don't need to overhaul your workflow to start noticing oral function. Next time a patient is in the chair and not actively speaking, look at:
The lips — comfortably closed, or habitually apart?
The tongue — where does it rest?
The teeth — clenched or separated at rest?
The breathing — comfortable through the nose, or not?
The swallow — does the tongue move forward, or do the lips and facial muscles overcompensate?
The history — prior oral habits, open bite, relapse, mouth breathing, speech or feeding concerns?
None of this diagnoses an orofacial myofunctional disorder on its own. It just gives you more information and sometimes that's exactly what leads to a useful referral.
The Goal Is Better Collaboration, Not More Referrals
Adding myofunctional therapy to your network shouldn't mean referring every patient by default. It should mean knowing when another perspective adds value. The strongest referral relationships are built on communication — the therapist understanding what you're trying to accomplish, you understanding what they're addressing, and both of you respecting the limits of your own role. That's what makes interdisciplinary care actually work, rather than just look good on paper.
A Whole-Mouth Approach to Dental Care
The mouth is a functional system — teeth, tongue, lips, jaw, muscles, breathing, swallowing, and habits all interacting. Orthodontics changes structure. Myofunctional therapy addresses function. Neither competes with the other; for the right patient, they're complementary.
If you're seeing recurring open bites, persistent oral habits, mouth breathing, low tongue posture, tongue thrust, or other functional concerns, a myofunctional evaluation may surface information your treatment plan is currently missing — without promising it'll prevent every case of relapse. The goal is simply a more complete, more collaborative plan around the patient.
FAQ: Myofunctional Therapy and Orthodontic Relapse
Does myofunctional therapy prevent orthodontic relapse?
No single intervention can guarantee that. Relapse is multifactorial, and myofunctional therapy addresses one contributing piece — oral function — not the full picture.
How do I know if a patient needs a myofunctional referral?
Look for persistent open-mouth posture, low or forward tongue rest position, tongue thrust during swallowing, difficulty maintaining lip closure, a history of oral habits, or a pattern of relapse after treatment.
Is myofunctional therapy evidence-based?
Research shows promising associations, particularly around open bite and tongue posture, but the evidence base still lacks enough high-quality randomized controlled trials to confirm effectiveness broadly. It's reasonable to consider, not a guaranteed fix.
When should therapy start relative to orthodontic treatment?
It depends on the patient before, during, or after treatment can all be appropriate. What matters most is coordination between the dentist/orthodontist and the therapist.
Ready to Build a Myofunctional Referral Pathway?
At MyoSpeech Solutions, we collaborate with dental and orthodontic professionals to support patients with orofacial myofunctional concerns — tongue posture, swallowing patterns, oral habits, lip function, mouth breathing, and related speech or feeding concerns.
If you're interested in building a referral relationship or want to learn more about how myofunctional therapy fits into your patients' care, book a discovery call with MyoSpeech Solutions.
Medical Disclaimer
This article is for educational purposes only and does not replace an individualized evaluation, diagnosis, or medical or dental advice. Myofunctional therapy is not appropriate for every patient, and treatment should be based on the patient's individual clinical needs and coordinated with appropriate healthcare professionals.